Incontinence Treatment Options: Your Complete Guide
Maybe you’ve started planning your day around the nearest bathroom. Maybe you cross your legs before you sneeze, wear a liner “just in case,” or avoid a workout class you used to enjoy. Some women notice a few drops when they laugh. Others feel a sudden urge and worry they won’t make it in time. Many do what they can to hide it and hope it will pass.
If that sounds familiar, you’re not overreacting, and you’re not alone. Leakage can feel private, frustrating, and oddly isolating. It can also make you second-guess your body in moments that should feel ordinary, like picking up your child, going for a walk, or sitting through a meeting without scouting the exit first.
The good news is simple. Incontinence is common, but it isn’t something you just have to live with. There are real incontinence treatment options, and many of them start with conservative care that helps you understand why the leakage is happening in the first place.
Your Guide to Reclaiming Control from Incontinence
One patient once described it this way: “I’m fine until I’m not.” She could get through most of the day without much trouble. Then a cough during a cold, a fast walk across a parking lot, or the sound of running water would catch her off guard. What bothered her most wasn’t only the leak. It was the constant mental load.
That’s often the hidden part of incontinence. You’re not just managing your bladder. You’re managing clothes, routes, timing, pads, hydration, and worry.

Leakage can happen after pregnancy, around menopause, during cancer recovery, alongside pelvic pain, or without an obvious reason at all. Sometimes the issue is weakness. Sometimes it’s poor timing or poor coordination. Sometimes the pelvic floor is too tight and can’t respond well under pressure. That’s why generic advice like “just do Kegels” often leaves people confused.
Why understanding comes first
The most helpful place to begin isn’t with fear of procedures or assumptions about aging. It’s with a clear question:
What kind of leakage are you having, and what’s driving it?
That answer shapes everything that follows. The right plan for someone who leaks when she jumps isn’t the same as the right plan for someone who feels a sudden overwhelming urge on the way to the bathroom.
Practical rule: The best treatment usually matches the pattern behind your symptoms, not just the fact that leakage exists.
What treatment can look like
Incontinence treatment options often include a mix of:
- Behavior changes like bladder training, timed voiding, and spotting bladder irritants
- Pelvic floor physical therapy to improve strength, endurance, relaxation, or coordination
- Medical support such as devices, medications, or procedures when conservative care isn’t enough
- Ongoing follow-up so the plan fits your life, goals, and body
You don’t need to figure all of this out alone. A good plan should feel understandable, practical, and adapted to your daily life. The goal isn’t perfection. The goal is more control, less fear, and a body that feels more predictable again.
Understanding the Types of Urinary Incontinence
You stand up from the couch and feel a sudden rush to the bathroom. Or you laugh at dinner and notice a few drops. Both are called incontinence, but they are not the same problem. That matters because the best treatment starts with understanding the pattern behind the leak.
Many people assume leakage is just “a weak bladder.” Usually, it is more specific than that. The bladder, pelvic floor, nerves, habits, and support tissues all play a role. If you want a fuller picture of the reasons symptoms can start, this guide on what causes urinary incontinence in women can help.
A useful way to begin is to sort leakage into the main types. You are not putting yourself into a permanent box. You are gathering clues, the same way a physical therapist looks at how, when, and why symptoms show up before choosing treatment.
Stress incontinence
Stress incontinence means urine leaks when pressure inside the abdomen rises faster than the pelvic floor can respond.
A simple comparison is a lid that does not close firmly enough during a sudden shake. Coughing, sneezing, laughing, lifting, or jumping all increase downward pressure. If the muscles and support tissues under the bladder do not provide enough support at that moment, leakage can happen.
Common triggers include:
- Coughing or sneezing
- Running, jumping, or exercise
- Lifting groceries or a child
- Laughing unexpectedly
This pattern often relates to support, timing, or coordination. It is not always just a strength issue.
Urge incontinence
Urge incontinence is the leakage that follows a strong, hard-to-delay need to urinate.
The bladder alarm is going off too early or too loudly. You may feel okay one moment, then suddenly feel like you have to get to a bathroom right now. Some people leak on the way there. Others can hold it sometimes but feel anxious because the urge is so intense.
You might notice it when:
- You put the key in the front door
- You hear running water
- You stand up after sitting
- The urge appears with very little warning
This pattern often overlaps with overactive bladder, which describes urgency, frequency, and sometimes urge leakage.
Urge leakage is not a willpower problem. It is a signaling problem.
Mixed incontinence
Mixed incontinence means you have both stress and urge symptoms.
For example, you might leak with a sneeze and also have those sudden, rushing urges that are hard to hold back. This is common. It can feel confusing at first because two different patterns are happening in the same body, but it also gives useful information. Treatment usually works best when both pieces are addressed instead of focusing on only one.
Overflow incontinence
Overflow incontinence usually feels like dribbling, incomplete emptying, or a bladder that still feels full after you urinate.
A bladder in this situation is more like a sink that keeps filling because it is not draining well. The leak is often not caused by a cough or a sudden urge. Instead, small amounts may spill out because the bladder is too full, the muscle is not squeezing well, or something is blocking normal emptying.
This type needs careful medical evaluation because the treatment approach is different from stress or urge incontinence.
A quick way to tell them apart
| Type | What it feels like | Common clue |
|---|---|---|
| Stress | Leakage with movement or pressure | “I leak when I cough or jump” |
| Urge | Sudden strong need to urinate | “I barely make it to the bathroom” |
| Mixed | Both stress and urge symptoms | “I have both patterns” |
| Overflow | Dribbling or incomplete emptying | “I never feel fully empty” |
If you are unsure which type fits, that is normal. Many people have overlapping symptoms, and the details matter. The goal is not to self-diagnose perfectly. The goal is to notice the pattern clearly enough that you can start with the right conservative treatment, especially options like pelvic floor therapy and bladder retraining, before jumping to more invasive care.
Starting with Conservative and Behavioral Strategies
The first step in treatment often has nothing to do with surgery and everything to do with patterns. Your bladder follows habits. Your pelvic floor responds to routines. Small changes can reveal a lot.
Many women start here because these strategies are practical, low-risk, and useful whether your symptoms are mild or more disruptive.
Start with a bladder diary
A bladder diary is one of the most helpful tools because it turns vague frustration into real information.
For a few days, write down:
- When you urinate
- When you leak
- What you were doing at the time
- What and when you drank
- Whether you felt urge, pressure, or both
This often uncovers patterns you wouldn’t otherwise notice. Maybe the leaks cluster in the afternoon. Maybe urgency spikes after coffee. Maybe you urinate “just in case” so often that your bladder has started expecting it.
Bladder training helps retrain the alarm system
Bladder training is useful when urgency is part of the picture. The idea is to gradually teach the bladder that it doesn’t need to sound the alarm so early.
That usually includes:
- Scheduled bathroom trips instead of going every time you think about it
- Urge control strategies like pausing, breathing, and staying still for a moment
- Gradual spacing between voids, based on what your body can tolerate
Bladder training doesn’t mean forcing yourself to suffer through intense urgency. It means building a calmer, more predictable rhythm over time.
Food and drink can affect symptoms
Not every bladder reacts the same way, but some women notice that certain inputs make symptoms worse.
A few common issues include:
- Caffeine because it can irritate the bladder for some people
- Alcohol because it may increase urgency or frequency
- Large fluid swings such as drinking very little all day, then a lot at once
- Habitual “just in case” voiding because it can train the bladder to signal sooner
If you’re trying to sort out symptom triggers, this page on what to avoid with pelvic floor dysfunction can help you think through everyday habits that may be adding strain.
A good behavioral plan shouldn’t make your world smaller. It should help you understand your triggers and give you more choices.
Why combinations often work better
Mixed incontinence can be confusing because one strategy rarely addresses the whole problem. That’s why combination treatment matters.
A major trial found that for mixed incontinence, combining bladder training with pelvic floor exercises led to “significantly fewer incontinence episodes, better quality of life, and greater treatment satisfaction” (study on combination therapy for mixed incontinence).
That makes clinical sense. If one part of your system needs better support and another part needs calmer signaling, your plan should address both.
What these first steps can and can’t do
Behavioral strategies help you build awareness and reduce triggers. They can also prepare you for pelvic floor therapy by making your symptoms more understandable.
They usually work best when you use them consistently and pair them with the right physical treatment when needed. If your pelvic floor isn’t coordinating well, your bladder diary can show the pattern, but it won’t fix the muscle issue by itself. That’s where targeted therapy becomes important.
The Power of Pelvic Floor Physical Therapy
You might be doing everything you were told to do. Crossing your legs before a sneeze. Mapping out bathrooms. Trying Kegels from a video. And still leaking.
That usually does not mean you failed. It often means the treatment did not match the reason your body is leaking.

Pelvic floor physical therapy starts with a different question. Instead of asking only, “How do we stop the leak?” it asks, “What is breaking down in the system when the leak happens?”
That distinction matters. The pelvic floor works like part of a pressure and support team with your diaphragm, abdominal wall, hips, and bladder. If one part is weak, late, tense, or poorly coordinated, leakage can show up even when you are trying hard to do the right exercise.
Pelvic floor therapy is more specific than “just do Kegels”
Many patients expect a quick lesson on squeezing. A real pelvic floor evaluation is much more detailed.
Your therapist may look at:
- Strength, to see whether the muscles can create enough support
- Endurance, to see whether they can keep working through a walk, workout, or full day
- Timing, because a contraction that happens after a cough is too late to help
- Coordination, since some people push down instead of lifting up
- Relaxation, because a muscle that never lets go cannot work well either
- Breathing and pressure control, especially during lifting, exercise, coughing, and getting up from a chair
This is one reason incontinence treatment should be patient-first. Two people can both say, “I leak when I exercise,” and need very different care. One needs strengthening. Another needs to stop gripping and learn how to relax first. A third needs to pair the pelvic floor with breath and core timing so pressure is managed before impact hits.
Why guided therapy often works better than trying on your own
Pelvic floor muscle training has good evidence behind it, especially when it is taught and progressed by a clinician. As noted earlier in the article, supervised programs tend to outperform general advice alone. That fits what pelvic floor therapists see every day.
Many women who say, “Kegels didn’t help,” were never shown how to identify the right muscles, how long to hold, when to relax, or how to use those muscles during a real-life trigger such as coughing or lifting a child.
Technique changes everything.
If you want a clear picture of the process, what to expect from pelvic floor physical therapy walks through how visits are typically structured.
What treatment usually includes
Treatment is usually a progression, not a generic handout.
-
Motor learning
First, you learn how to find and feel the pelvic floor correctly, often in sync with your breathing. -
Strengthening or down-training
If the muscles are underactive, the plan builds support. If they are overactive, the plan focuses on letting go, reducing guarding, and restoring normal movement. -
Functional practice
Then you apply the skill to the moment that matters. Coughing, lifting, rolling in bed, running, jumping, or getting to the bathroom without rushing and bearing down. -
Bladder and habit support
Pelvic floor control is often paired with urge-suppression strategies, bladder retraining, and changes in how pressure is managed during daily tasks. -
Home practice
The best home plan is short, specific, and realistic enough that you will do it.
Tools that may help along the way
Some patients benefit from biofeedback, which gives real-time information about muscle activity. That can help if you are not sure whether you are lifting, clenching your glutes, or pushing downward instead.
In some cases, therapists or medical providers may also use electrical stimulation as an added tool. It is not the starting point for everyone, and it is not a replacement for skilled assessment. It can be useful when it matches the problem being treated. A clinical review in StatPearls describes pelvic floor muscle therapy as a first-line conservative treatment for stress and mixed incontinence and notes that adjuncts such as biofeedback or electrical stimulation may be used in selected cases (StatPearls review of stress urinary incontinence management).
For some readers, seeing movement and technique explained visually makes the process feel much less abstract.
What personalized care looks like in real life
A runner leaking during hill sprints does not need the same program as a new mother leaking when she stands up with a full bladder. A woman recovering from gynecologic cancer treatment may need a gentler plan that also accounts for scar mobility, tissue sensitivity, and fatigue.
That is why pelvic floor PT is often one of the most effective conservative options to try before moving to more invasive treatment. It helps identify the reason behind the symptom, then builds a plan around your body, your triggers, and your goals.
A local example is Lake City Physical Therapy, which offers pelvic health physical therapy for concerns including incontinence, prolapse, and postpartum recovery.
The goal of pelvic floor PT is simple. Help your body handle daily life with fewer leaks, less fear, and less mental energy spent planning around your bladder.
Exploring Medical Devices and Procedural Options
Sometimes conservative treatment reduces symptoms but doesn’t fully solve the problem. Sometimes urge symptoms remain strong, or support issues need another layer of management. That’s when it helps to understand the next tier of incontinence treatment options.
These aren’t “last resort” tools in every case. They’re different tools for different patterns.
Pessaries and support devices
A pessary is a removable device placed in the vagina to support pelvic organs and sometimes reduce stress-related leakage.
This option can make sense when the problem involves support, prolapse, or leakage during activity. Some women like it because it doesn’t require surgery and can be used situationally, such as during exercise or long workdays.
It’s still important to talk through fit, comfort, and side effects with a medical provider. A device that helps one person may irritate another.
Urethral bulking agents
Bulking procedures are designed to improve closure around the urethra. They’re usually considered when stress incontinence is the main issue and conservative treatment hasn’t been enough.
In simple terms, this approach tries to help the “seal” close more effectively. It’s procedure-based care, so candidacy and expectations should be discussed carefully with a physician.
Botox for urge incontinence
For urge incontinence linked to overactive bladder, onabotulinumtoxinA (Botox) injections into the bladder muscle are a recognized option.
Clinical trials show that 47% to 72% of patients had at least a 50% reduction in leakage episodes at 12 weeks, and about 27% achieved complete dryness (AAFP review of urinary incontinence treatment and Botox outcomes).
Botox works by calming overactive bladder muscle contractions. It’s often considered when urgency and urge leakage continue despite more conservative care.
A realistic conversation should also include downsides. Temporary urinary retention can happen, which is why physicians screen for risk and explain follow-up needs before treatment.
Sacral neuromodulation
Sacral neuromodulation is sometimes described as a pacemaker for the bladder. It uses implanted stimulation to influence the nerves involved in bladder control.
This option is more advanced than office-based behavioral or exercise treatment. It’s generally considered when symptoms are persistent and other approaches haven’t helped enough. For the right patient, it can be meaningful. For others, it may be more intervention than they need.
Choosing the right level of treatment
A helpful way to think about procedural care is to ask three questions:
| Question | Why it matters |
|---|---|
| What type of leakage do I have most often? | Stress and urge symptoms usually respond to different tools |
| What have I already tried well? | A treatment shouldn’t replace good conservative care if that care hasn’t been fully tested |
| What trade-offs am I comfortable with? | Convenience, repeat treatments, discomfort, retention risk, and follow-up all matter |
Medical options can be useful, but they work best when they’re chosen for the right reason. A treatment that sounds less invasive isn’t automatically more appropriate. Matching the intervention to the symptom pattern is what matters most.
Creating Your Personal Treatment Plan
Often, individuals don’t need more information. They need a clearer way to decide what applies to them.
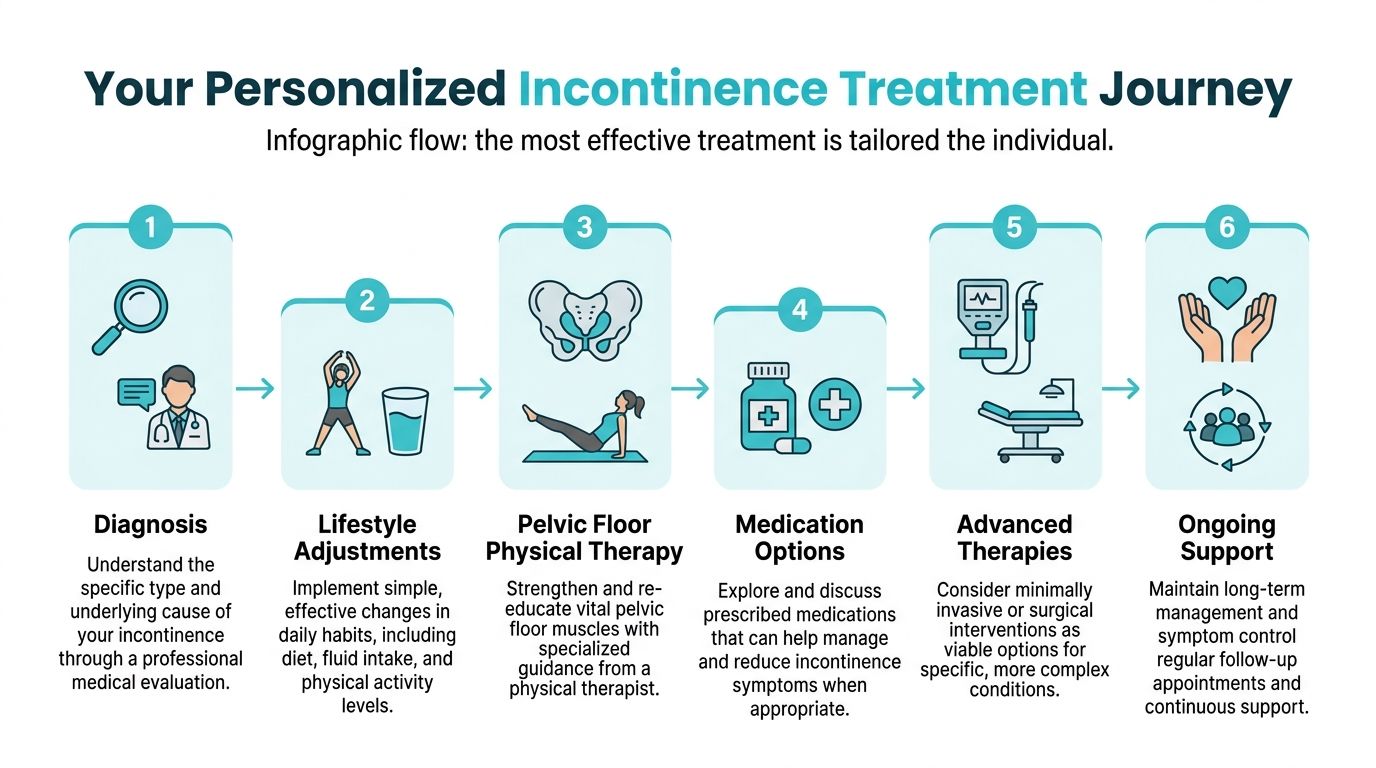
The best plan usually starts with your symptom pattern, then layers treatment in a logical order. That order matters because it keeps you from skipping past conservative care that may help, while also avoiding the frustration of trying random strategies without a diagnosis.
A simple decision path
If you mainly leak with coughing, sneezing, lifting, or exercise, start by thinking stress incontinence. Pelvic floor assessment, pressure management, and movement retraining usually belong near the top of the list.
If your main problem is strong urgency, frequent bathroom trips, or leaking on the way to the toilet, urge-focused strategies become more relevant. Bladder training, urge suppression skills, and medical management may all play a role.
If you have both patterns, your plan may need to combine approaches instead of picking sides.
Why evaluation matters so much
Many online guides fall short. They list options, but they don’t explain how a clinician decides among them.
A key gap in many patient resources is that selection among non-surgical options depends on a clinical assessment of muscle strength, urethral mobility, and prolapse severity, which is why evaluation by a pelvic floor specialist is so important (UCLA Health overview of urinary incontinence treatment selection).
That means two women with “the same leak” may need very different first steps.
Clinical takeaway: Don’t choose a treatment only by reading a list of options. Choose it based on the body system that’s driving your symptoms.
Questions worth asking at your visit
Bring these with you if you tend to freeze up during appointments:
- What type of incontinence do my symptoms suggest?
- Do my pelvic floor muscles seem weak, overactive, poorly coordinated, or a mix?
- Should I start with bladder training, pelvic floor PT, or both?
- Are there signs of prolapse or incomplete emptying?
- At what point would a device, medication, or procedure make sense?
It can also help to keep communication simple outside the clinic. For patients juggling work, caregiving, and appointments, tools that support streamlined healthcare communication can make it easier to manage reminders, follow-ups, and care tasks without adding more mental clutter.
Think in stages, not in failure
Needing more than one treatment doesn’t mean you failed the first one. It often means your symptoms have more than one contributor.
A smart plan is layered. It starts with diagnosis, uses conservative care well, and escalates only when the pattern and response suggest it’s appropriate. That’s how treatment becomes more precise and less overwhelming.
Frequently Asked Questions about Incontinence Treatment
Is incontinence just a normal part of aging
No. It becomes more common across life stages, but “common” and “normal” aren’t the same. Leakage is a symptom, not a personality trait or a life sentence. Aging, childbirth, menopause, surgery, training load, pelvic pain, and medical conditions can all contribute. That still doesn’t mean nothing can be done.
How do I bring this up without feeling embarrassed
Keep it simple and direct. You don’t need the perfect script.
Try one of these:
- “I’m leaking urine when I cough or exercise.”
- “I’ve started having sudden urges and I’m not always making it to the bathroom.”
- “This is affecting my daily life, and I want to talk about treatment options.”
Clinicians hear this often. What feels personal to you is also a common medical concern, and naming it clearly helps you get useful care faster.
If you’re not sure where to begin, write down your symptoms before the appointment and read from the note. That counts.
Will insurance cover pelvic floor physical therapy
Coverage varies by plan, referral requirements, deductible status, and location. The practical move is to call your insurer and ask specific questions about pelvic floor physical therapy, visit limits, copays, and whether a referral is needed.
The clinic can often help you understand scheduling and billing steps, but your insurance company is the one that can confirm your benefits.
How long does it take to see results
That depends on the type of leakage, how long it’s been happening, whether the issue is strength or coordination, and how consistently you follow the plan.
Some women notice early changes once they understand their triggers and start practicing the right strategies. Others need a longer course of care, especially if symptoms are complex or have been present for a long time. Improvement usually comes from repetition, accuracy, and matching the treatment to the problem.
What if I already tried Kegels and they didn’t help
That doesn’t automatically mean pelvic floor therapy won’t work. It may mean the exercises weren’t the right fit, weren’t taught well, or weren’t what your body needed most. Some people need relaxation before strengthening. Some need urge training. Some need to coordinate breath and pressure before any strengthening makes sense.
When should I seek help sooner
Reach out promptly if leakage is worsening, if you feel you can’t empty well, if you have significant pelvic pressure, pain, or recurrent urinary concerns, or if the problem is limiting exercise, work, travel, intimacy, or sleep. You don’t need to wait until symptoms become severe to deserve care.
If you’re ready to stop guessing and start with a clear, individualized plan, Lake City Physical Therapy offers pelvic health care for women dealing with incontinence, prolapse, postpartum recovery, pelvic pain, and related concerns. A focused evaluation can help identify what type of leakage you’re experiencing, what may be contributing to it, and which conservative treatment options make the most sense for your next step.

